Lucy, 31 - Leeds, took the prescribed Glucophage dose with her evening meal for several weeks. The first days brought loose stools and a metallic taste, but the stomach symptoms eased after the regimen was adjusted. She found that taking it halfway through the meal was more comfortable than taking it before eating.
Leeds Several weeks 24 Oct 2026
Glucophage
Glucophage is used to manage type 2 diabetes when lifestyle measures alone do not provide adequate blood-glucose control. Its active ingredient, metformin, belongs to the biguanide class and lowers…
Glucophage is used to manage type 2 diabetes when lifestyle measures alone do not provide adequate blood-glucose control. Its active ingredient, metformin, belongs to the biguanide class and lowers glucose production by the liver while improving the body’s response to insulin. It is usually taken as tablets with food, with the regimen confirmed by a healthcare professional before treatment begins.
Product information
Glucophage is the brand name associated with metformin, an antidiabetic medicine in the biguanide class. Metformin does not stimulate the pancreas to release large amounts of insulin. Its main action is to reduce excess glucose production by the liver and help tissues respond more efficiently to the insulin already present.
What it is used for
Glucophage is primarily used for type 2 diabetes mellitus. It helps lower blood glucose and may contribute to a reduction in HbA1c, the laboratory measure that reflects average glucose exposure over approximately two to three months.
The treatment goal is individual. HbA1c targets depend on age, duration of diabetes, kidney function, risk of hypoglycaemia, pregnancy status and other health conditions. A single target does not suit every adult.
Metformin may be prescribed alone when the rise in glucose is modest or combined with other therapies when additional reduction is required. It does not replace dietary planning, movement or monitoring recommended for the individual treatment plan.
Prediabetes is a separate metabolic state in which glucose levels are above the usual range but below the diagnostic threshold for diabetes. Metformin is sometimes used off-label for selected people with prediabetes, such as those with a high risk of progression, but this is a clinical decision rather than an automatic indication.
Gestational diabetes requires specialist management because glucose targets and medicine choices change during pregnancy. Metformin may be used in some pregnancy-related diabetes pathways, but the decision depends on obstetric assessment, glucose results and local clinical guidance. It should not be started, stopped or adjusted for gestational diabetes without the maternity or diabetes team.
The World Health Organization describes type 2 diabetes as a chronic condition involving impaired insulin action and progressive difficulty maintaining normal glucose levels. Metformin addresses insulin resistance and excessive hepatic glucose production, but it does not cure the underlying tendency towards diabetes [1].
Ingredients
Glucophage contains metformin as its active ingredient. Metformin belongs to the biguanide class of antidiabetic medicines and is supplied as tablets.
How it affects the body
Metformin reduces excess glucose production by the liver and improves the response of tissues to insulin already present in the body. It lowers circulating blood glucose without directly stimulating the pancreas to release large amounts of insulin.
How to use it
Glucophage is supplied as tablets. The regimen for the chosen strength must be confirmed with a healthcare professional before starting. The appropriate amount depends on blood-glucose results, kidney function, previous metformin exposure, other medicines and tolerability.
The practical principles are:
- Take the prescribed tablets with food or immediately after food.
- Swallow tablets with water.
- Take doses at the same times each day.
- Do not double the next dose after a missed tablet.
- If a dose is missed, take the next scheduled dose unless a clinician has given different instructions.
- Do not change the dose because a single glucose reading is higher or lower than expected.
- Tell the prescriber about vomiting, diarrhoea, dehydration, fever or reduced fluid intake.
Glucophage tablets should not be crushed or chewed unless the specific formulation has been confirmed as suitable for alteration. Sustained-release tablets are designed to release metformin gradually. Damaging the tablet can change its release pattern and may increase gastrointestinal symptoms.
A common practical mistake is taking metformin on an empty stomach to “make it work faster”. This does not improve glucose control and can make nausea or diarrhoea more troublesome.
Comparison
The most useful distinction is the mechanism, not the brand name. Metformin lowers hepatic glucose output and improves insulin sensitivity, whereas several other medicine categories work by increasing insulin availability, delaying glucose absorption or increasing glucose loss through the kidneys.
| Approach | Main action | Main limitation |
|---|---|---|
| Metformin | Reduces liver glucose production and improves insulin sensitivity | Gastrointestinal effects; kidney function affects suitability |
| Insulin-releasing medicines | Increase insulin release from pancreatic beta cells | Greater hypoglycaemia risk and possible weight gain |
| SGLT2 inhibitors | Increase urinary glucose excretion | Genital infections, dehydration and other class-specific risks |
Metformin is often selected early because it does not usually cause hypoglycaemia when used alone and does not generally promote weight gain. Its disadvantages include gastrointestinal intolerance, the need to assess kidney function and the possibility of vitamin B12 depletion during prolonged use.
An SGLT2 inhibitor may be favoured when heart failure or chronic kidney disease is a major treatment consideration. An insulin-releasing medicine may be considered when a rapid glucose-lowering effect is needed, though the clinical trade-offs differ. The final choice depends on glucose levels, cardiovascular and kidney health, weight goals, pregnancy status and current medicines.
Common mistakes
Several practical errors can reduce tolerability or make glucose readings difficult to interpret:
- Taking tablets without food. This can worsen nausea and diarrhoea.
- Stopping after a few days of stomach upset. Mild symptoms may settle, while persistent or severe symptoms need review and a treatment adjustment.
- Doubling a missed dose. This increases gastrointestinal exposure without reliably improving glucose control.
- Crushing a sustained-release tablet. Altered release can increase side effects.
- Continuing through severe dehydration. Vomiting and diarrhoea can create conditions in which metformin becomes unsafe.
- Assuming metformin prevents every form of diabetes. It treats insulin resistance and high glucose; it does not remove the need for lifestyle measures or monitoring.
- Ignoring numbness or unusual tiredness. These symptoms can occur for many reasons, including vitamin B12 deficiency during long-term therapy.
- Changing the dose after one high reading. Glucose varies with illness, meals, sleep, stress and activity.
One easily missed detail is the timing of blood tests. HbA1c reflects a longer period and cannot be interpreted in the same way as a single fasting glucose result.
Who should not use it
Glucophage is not suitable in these situations
- Severe kidney impairment.
- Acute kidney injury.
- Severe dehydration from vomiting, diarrhoea or inadequate fluid intake.
- Metabolic acidosis, including diabetic ketoacidosis.
- Severe infection or circulatory collapse with reduced tissue oxygenation.
- Severe liver disease where lactic acidosis risk is increased.
- Previous serious hypersensitivity to metformin or an excipient in the prescribed tablet.
- Situations requiring urgent iodinated contrast imaging when the clinical team instructs temporary interruption.
Metformin may interact clinically with medicines that impair kidney function or cause dehydration. Examples include some diuretics, non-steroidal anti-inflammatory drugs and medicines affecting blood pressure or renal blood flow. This does not mean every combination is prohibited, but the combination may require closer monitoring.
When this is not for you
Alcohol can increase the risk of lactic acidosis, especially with binge drinking, poor food intake, liver disease or dehydration. Heavy alcohol consumption should be disclosed before treatment.
Kidney function requires attention because metformin is eliminated mainly through the kidneys. A falling estimated glomerular filtration rate may require dose adjustment or discontinuation. Iodinated contrast procedures can also require temporary interruption, depending on renal function and the type of examination.
Pregnancy and breastfeeding require an individual assessment. Metformin is used in some pregnancy-related diabetes pathways, while the benefits and alternatives depend on the clinical situation. The prescriber should know about pregnancy, planned pregnancy or breastfeeding before the regimen is changed.
Possible side effects
The most frequent adverse effects involve the digestive system. Nausea, loose stools, diarrhoea, abdominal cramping, bloating and reduced appetite may occur when treatment begins or after a dose increase. A metallic taste is also reported by some patients.
These effects often improve when the dose is increased gradually and tablets are taken with meals. Some people tolerate a sustained-release formulation better than standard-release tablets, although the formulation must match the prescribed regimen.
Typical tolerability problems include:
- Nausea or queasiness.
- Diarrhoea or softer stools.
- Abdominal discomfort.
- Bloating or increased wind.
- Reduced appetite.
- Metallic taste.
- Indigestion.
Metformin alone rarely causes hypoglycaemia because it does not directly force the pancreas to release insulin. Low blood glucose becomes more plausible when metformin is combined with insulin, sulfonylureas or other treatments that can lower glucose independently.
Long-term metformin therapy can reduce vitamin B12 absorption. The risk is higher with prolonged treatment, higher doses, pre-existing low B12 levels, anaemia, vegetarian or vegan diets, malabsorption disorders and medicines that also affect B12 status. Symptoms such as persistent tiredness, a sore tongue, numbness, pins and needles or balance problems warrant clinical assessment.
Lactic acidosis is rare but serious. The risk increases with severe kidney impairment, acute dehydration, serious infection, tissue hypoxia, heavy alcohol intake and some situations involving reduced oxygen delivery. The MHRA safety information supports careful assessment of renal function and temporary interruption in clinical situations that may cause dehydration or acute kidney deterioration [2].
What doctors say
In clinical practice, doctors usually judge metformin by sustained glucose control rather than by a dramatic day-to-day sensation. Many patients do not feel a noticeable change after the first tablet, even when the medicine is beginning to influence fasting glucose.
The most useful follow-up information includes home glucose readings when requested, HbA1c, kidney function, digestive tolerability, body weight and any symptoms of low blood glucose when other medicines are also used. These measures show whether control is improving and whether treatment remains tolerable. Kidney results help determine whether the regimen is still appropriate. HbA1c shows the longer-term pattern, while home readings can reveal day-to-day variation. Symptoms and concurrent medicines may explain changes that glucose results alone do not show.
Doctors also look for patterns. A patient who has diarrhoea after every dose may need slower dose escalation, meal-based administration or a different release formulation. A patient with persistent fatigue or new neurological symptoms may need assessment for vitamin B12 deficiency rather than an automatic assumption that diabetes has worsened.
A clinician would also ask about non-prescription painkillers, alcohol intake, acute infections and fluid loss. These details can change the risk profile even when the Glucophage dose has remained unchanged.
The HbA1c response should be assessed over an appropriate interval rather than after a few isolated readings. NICE guidance places glucose targets within an individualised diabetes plan, taking account of hypoglycaemia risk and patient circumstances [3].
Common questions
Which condition rules out Glucophage?
Severe kidney impairment, diabetic ketoacidosis and metabolic acidosis rule out routine Glucophage treatment. Acute dehydration, serious infection with reduced circulation and some urgent contrast-imaging situations can also require interruption or specialist review. The EMA product information identifies renal function and lactic-acidosis risk as central safety considerations for metformin. These principles remain clinically relevant in 2026 [4].
How does Glucophage differ from an insulin-releasing treatment?
Glucophage contains metformin, which mainly reduces liver glucose production and improves insulin sensitivity. Insulin-releasing treatments stimulate pancreatic insulin secretion and can therefore carry a greater risk of hypoglycaemia. The choice depends on HbA1c, kidney function, cardiovascular health, weight considerations and other medicines. NICE guidance updated in 2022 for type 2 diabetes care in the UK places treatment selection within an individualised risk-benefit plan.
How soon can a person notice an effect?
Some people see lower fasting glucose readings within days, while the full HbA1c response takes longer because HbA1c reflects average glucose exposure over roughly two to three months. Digestive side effects may appear before any noticeable glucose improvement. The WHO described type 2 diabetes in 2023 as a chronic condition requiring ongoing management rather than a short course of treatment. A glucose result should be interpreted alongside the planned monitoring schedule.
Which symptoms require stopping and seeking urgent medical help?
Urgent assessment is needed for severe weakness, confusion, marked drowsiness, deep or rapid breathing, persistent vomiting, severe abdominal pain or inability to maintain fluids. These symptoms may indicate serious illness, dehydration or the rare complication of lactic acidosis. The MHRA identified in 2015 acute conditions that impair renal function or tissue oxygenation as important risk settings for metformin. Do not take additional doses while seeking urgent instructions if severe dehydration or serious illness is present.
What happens after stopping Glucophage, and is tapering needed?
Metformin is not usually tapered in the same way as medicines that cause physiological withdrawal. Stopping it can allow blood glucose to rise again because the underlying insulin resistance and excessive hepatic glucose production remain. The clinical reason for stopping matters, especially when kidney function has changed or dehydration is present. The EMA product information from 2018 supports restarting only when the relevant clinical circumstances and renal function have been reassessed.
Do you offer anonymous delivery?
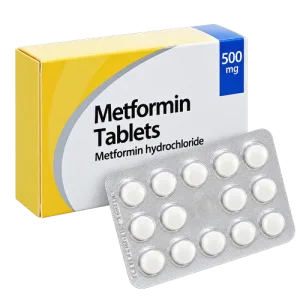
Your order will be securely packed and shipped within 24 hours. This is exactly what your package will look like (images of an actual item sent). It has the size and look of a regular private letter (24x11x0.7 cm) and its contents cannot be seen.
Comparison
Empagliflozin
Forxiga
Glucophage Current
Metformin
Reviews: Glucophage
Based on 4 reviews
Helen, 33 - Swansea, used the prescribed metformin dose as part of a type 2 diabetes plan for several weeks. Her glucose readings became more consistent over the following weeks, although she felt less hungry than usual at first. She disliked the early nausea and needed a slower increase agreed with her clinician.
Swansea Several weeks 30 Oct 2026Gemma, 52 - Stoke-on-Trent, had taken the prescribed Glucophage dose for a longer period alongside another glucose-lowering treatment. She reported good day-to-day control but later developed persistent tiredness and tingling in her feet. Testing identified a vitamin B12 issue that required follow-up rather than simply increasing diabetes medicine.
Stoke-on-Trent A longer period 4 Oct 2026Louise, 42 - Liverpool, had taken the prescribed Glucophage dose for several weeks before stopping during a period of vomiting because she could not keep fluids down and contacted her diabetes team. She later restarted according to their instructions. Her main complaint was that the tablet was easy to forget when her meals changed at weekends.
Liverpool Several weeks 12 Oct 2026Sources
- World Health Organization (2023). Diabetes: Key facts.
- Medicines and Healthcare products Regulatory Agency (2015). Metformin and risk of lactic acidosis in renal impairment.
- National Institute for Health and Care Excellence (2022). Type 2 diabetes in adults: management.
- European Medicines Agency (2018). Metformin-containing medicines: recommendations on use in patients with reduced kidney function.