The first week brought loose stools, especially after breakfast. Taking it with a full meal helped, and the symptoms settled after the dose was adjusted. My home readings became steadier by the fourth week.
Glasgow Six weeks 30 Sept 2026
Metformin
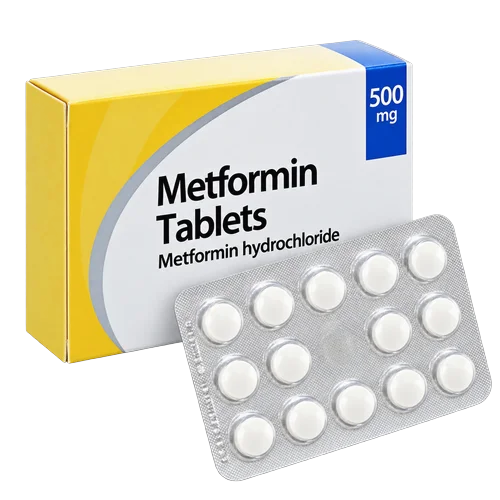
Metformin is a tablet containing metformin hydrochloride for adults with type 2 diabetes. It may help lower blood glucose when diet and activity changes alone do not achieve the agreed target.
Product information
Metformin belongs to the biguanide class of glucose-lowering medicines. The active substance is metformin hydrochloride, supplied as tablets. It is widely used as a first-line treatment for type 2 diabetes mellitus because it lowers blood glucose without directly forcing the pancreas to release more insulin. How much to use and how often depends on the purpose of use and is agreed with a doctor or pharmacist.
What it is used for
Adults with type 2 diabetes may be prescribed Metformin when diet and activity changes alone do not control blood glucose.
Metformin may be used alone or alongside other glucose-lowering treatments when blood glucose remains above the agreed target. The choice depends on cardiovascular disease, heart failure, chronic kidney disease, body weight, hypoglycaemia risk, treatment preferences and kidney function.
Polycystic ovary syndrome is one setting in which metformin may be considered, especially when insulin resistance or impaired glucose regulation is present. It may support metabolic management, but it does not replace treatment directed at menstrual symptoms, fertility, acne or excess hair growth.
Gestational diabetes requires an individual plan. Insulin remains an important treatment option, and pregnancy-related prescribing decisions depend on glucose readings, gestational age, maternal health and local guidance. Metformin may be considered in some circumstances, but its use should be decided by the maternity-diabetes team.
Metformin has also been studied in other insulin-resistance conditions, including hidradenitis suppurativa. Evidence and clinical practice vary, so treatment should be directed by the clinician managing that condition rather than copied from a diabetes regimen.
Ingredients
The active substance is metformin hydrochloride, supplied as tablets. How much to use and how often depends on the purpose of use and is agreed with a doctor or pharmacist.
How it affects the body
Metformin lowers circulating glucose through several complementary pathways. Its main action is to reduce hepatic gluconeogenesis, which means the liver makes and releases less new glucose between meals and overnight.
The medicine also improves insulin sensitivity. Muscle cells can respond more effectively to the insulin already present, allowing greater movement of glucose from the bloodstream into tissues. Metformin does not replace insulin and does not normally create a large increase in insulin secretion.
A further effect occurs in the intestine, where metformin can modestly reduce glucose absorption and influence gut-related metabolic signalling. The combined result is lower fasting glucose and improved after-meal glucose control.
The scientific explanation is more complex than a single pathway. Metformin influences cellular energy sensing, including pathways associated with AMP-activated protein kinase, while its clinical effect depends on the liver, intestine, kidneys and insulin-sensitive tissues working together. The EMA describes metformin as a glucose-lowering medicine whose principal clinical action is reduction of hepatic glucose production [2].
How to use it
The tablet should be taken exactly at the dose and frequency agreed with the prescribing clinician or pharmacist. The correct regimen depends on kidney function, blood glucose results, gastrointestinal tolerance and any other diabetes medicines being used.
Metformin is supplied in tablet form. How much to use and how often depends on the purpose of use and is agreed with a doctor or pharmacist.
Prescribed use generally follows these principles:
- Take the tablet by mouth with food or just after food.
- Swallow it with water unless a prescriber has given different instructions.
- Take doses at consistent times each day.
- Do not crush or chew a modified-release tablet if a modified-release formulation has been prescribed.
- If a dose is missed, take the next dose at the usual time unless a healthcare professional has given different instructions.
- Do not take two doses together to compensate for a missed tablet.
Metformin should not be stopped abruptly without a treatment plan when it is being used for diabetes. Blood glucose can rise when regular treatment is interrupted, especially during illness or when other glucose-lowering medicines are also involved.
NICE guidance recommends metformin as a core treatment for many adults with type 2 diabetes, alongside nutrition, physical activity and individualised cardiovascular-risk management [1].
Comparison
Metformin is an oral, single-ingredient glucose-lowering treatment. Unlike combination approaches, it contains one active substance, while the choice between treatments depends on factors such as kidney function, cardiovascular disease, body weight and hypoglycaemia risk.
Common mistakes
Common problems arise from changing the regimen without accounting for meals, illness or other medicines.
- Taking the tablet on an empty stomach and then stopping permanently after one episode of nausea.
- Doubling the next dose after forgetting a tablet.
- Continuing metformin through severe vomiting or diarrhoea without seeking advice.
- Assuming metformin cannot cause hypoglycaemia when it is combined with gliclazide or insulin.
- Missing kidney-function checks during long-term treatment.
- Ignoring new pins and needles because they are assumed to be diabetic neuropathy.
- Crushing a modified-release tablet, which can alter its release characteristics.
- Stopping treatment before a scan or surgery without receiving a restart plan.
- Drinking heavily while dehydrated or acutely unwell.
One overlooked detail is that an ordinary stomach illness can become more relevant when metformin is involved. Reduced fluid intake and declining kidney function may increase the risk of drug accumulation.
When this is not for you
Metformin may need temporary interruption during significant vomiting, diarrhoea, dehydration or a serious acute illness. A clinician may also advise a short pause around certain contrast procedures, followed by reassessment of kidney function before treatment restarts.
Possible side effects
Nausea, loose stools, abdominal discomfort, bloating and reduced appetite are the most familiar adverse effects of metformin. They often appear during the first days or weeks of treatment, after a dose increase, or when a person takes the tablet without food.
Slow dose escalation allows the digestive system more time to adapt. A prescriber may begin with a lower daily exposure and increase it in stages, depending on glucose results and tolerance. Modified-release metformin can reduce gastrointestinal symptoms for some people, although it does not remove the possibility completely.
In clinical practice, diarrhoea is sometimes blamed on a meal or stomach infection when it began soon after a metformin increase. A persistent change deserves review because dehydration can affect kidney function and alter how safely metformin can be used.
Practical measures include:
- Taking each dose with food.
- Avoiding sudden dose increases.
- Drinking enough fluid during ordinary daily activity.
- Reporting persistent vomiting or diarrhoea.
- Discussing a modified-release formulation if symptoms continue.
Severe abdominal pain, unusual weakness, rapid breathing, marked drowsiness or feeling very unwell needs urgent medical assessment. These symptoms can occur with several illnesses, including dehydration and serious metabolic complications.
Lactic acidosis is rare but serious. It involves an abnormal rise in lactate and blood acidity and is more likely when metformin accumulates because the kidneys cannot clear it adequately. The MHRA has highlighted the need for appropriate kidney-function assessment and careful management during illness, dehydration and other situations that increase risk [3].
Long-term metformin treatment is associated with reduced vitamin B12 levels in some patients. The likelihood increases with higher cumulative exposure, prolonged treatment, pre-existing low B12 levels, malabsorption, restrictive diets and other risk factors.
Possible manifestations include persistent tiredness, a sore or smooth tongue, mouth ulcers, pale skin, pins and needles, reduced balance or changes in memory. Nerve symptoms can be mistaken for diabetic neuropathy, so the distinction matters.
The MHRA advises checking vitamin B12 in people with symptoms or risk factors and considering periodic monitoring in those receiving long-term metformin [4]. A low result can usually be investigated and treated while diabetes management continues, depending on the clinical assessment.
Alcohol can complicate glucose control and may increase dehydration risk. Heavy or binge drinking also raises concern about lactic acidosis, especially when kidney or liver function is impaired.

What doctors say
Clinicians generally judge Metformin by sustained glucose improvement, tolerance, kidney function and the patient’s wider cardiovascular risk. A lower glucose reading on its own does not show whether the entire treatment plan is working.
Doctors often emphasise that gastrointestinal symptoms can improve after gradual dose adjustment. Persistent symptoms, weight loss, dehydration or a sudden decline in appetite need assessment rather than repeated self-adjustment.
A practical prescribing conversation usually covers kidney function, alcohol intake, recent illness, planned surgery, contrast imaging and other medicines. The care team may also review vitamin B12 risk during long-term treatment, following MHRA safety advice.
Common questions
How should Metformin tablets be stored at home and while travelling?
Keep Metformin tablets in a dry place at ordinary room temperature, away from excessive heat and moisture. During travel, keep them in their original dispensing container and carry enough for the planned period, with extra arrangements made if travel is delayed. The NHS and MHRA advise maintaining a reliable medicine supply during travel and avoiding storage conditions that can damage tablets. These principles remain relevant in 2026.
What should be discussed with a doctor before starting Metformin?
Discuss kidney function, liver disease, heavy alcohol intake, recent dehydration, planned surgery and any scan involving iodinated contrast. Mention medicines that may affect kidney function or glucose control, as well as previous problems with metformin. NICE guidance updated in 2022 places kidney assessment and individualised diabetes treatment at the centre of prescribing decisions.
Can Metformin affect driving, concentration or work with machinery?
Metformin alone does not usually impair concentration or cause hypoglycaemia. Driving risk can change when it is combined with insulin or gliclazide, because those treatments can lower blood glucose. The DVLA's 2025 guidance and UK diabetes guidance expect drivers to understand their treatment-related hypoglycaemia risk, so the medicine combination matters more than metformin alone.
Can Metformin be used during pregnancy or breastfeeding?
Pregnancy treatment should be planned with the maternity-diabetes team because glucose targets and treatment choices change during pregnancy. Insulin is an established option for gestational diabetes, while metformin may be considered in selected circumstances after a clinical assessment. NICE guidance for diabetes in pregnancy, reviewed in 2020, supports individualised decisions that account for maternal glucose control and treatment risks.
Which diet, exercise and habits help or hinder Metformin treatment?
Regular meals, gradual increases in physical activity and a diet suited to diabetes management can support glucose control. Skipping meals, binge drinking, dehydration and sudden strenuous exercise may destabilise glucose readings or worsen gastrointestinal symptoms. The WHO's 2024 guidance describes physical activity and dietary quality as central parts of type 2 diabetes care, not optional additions to medicine.
How soon can the effect of Metformin become noticeable?
Glucose readings may begin to change during the first one to two weeks, although the full assessment usually takes longer and depends on the prescribed regimen. A clinician may review home readings and laboratory markers such as HbA1c over several weeks or months. The American Diabetes Association’s 2024 Standards of Care uses HbA1c review at defined clinical intervals to judge whether treatment goals are being met.
Is Metformin suitable for older adults?
Older adults can use Metformin when kidney function, hydration and general health support treatment. Dosing may need extra care during acute illness, reduced appetite, weight loss or changes in renal function. The British Geriatrics Society's 2024 guidance stresses individual assessment in older people, since frailty, multiple medicines and kidney impairment can alter the balance of benefit and risk.
Do you offer anonymous delivery?
Your order will be securely packed and shipped within 24 hours. This is exactly what your package will look like (images of an actual item sent). It has the size and look of a regular private letter (24x11x0.7 cm) and its contents cannot be seen.
Comparison
Empagliflozin
Forxiga
Glucophage
Metformin Current
Reviews: Metformin
Based on 4 reviews
I tolerated the tablets reasonably well and did not have any low-sugar episodes while using metformin alone. I still felt tired, so my practice checked vitamin B12 and kidney function rather than assuming it was simply age.
Middlesbrough Three months 9 Oct 2026The medicine fitted into my routine, but diarrhoea returned when I restarted it after missing several days. I needed a slower restart and more attention to taking it with food.
Bristol Two months 15 Oct 2026My glucose readings improved after the first few weeks. I had expected immediate results and became frustrated, but the gradual change made more sense once my clinician explained how the medicine works.
Reading Four months 29 Oct 2026Sources
- NICE (2022). Type 2 diabetes in adults: management (NG28).
- EMA (2019). Summary of Product Characteristics (SmPC) — metformin-containing medicinal products.
- MHRA (2016). Metformin and the risk of lactic acidosis.
- MHRA (2022). Metformin and reduced vitamin B12 levels: new advice for monitoring patients at risk.